After significant weight loss, loose skin rarely follows a single pattern. In my practice, patients who have experienced significant weight loss, whether through bariatric surgery, medication assisted weight loss, or lifestyle change, often present with extensive excess skin that runs in more than one direction. Skin hangs vertically at the front of the abdomen, laxity runs horizontally around the waist, and the excess continues past the flanks into the lower back and buttock region.

No single standard technique treats all of that. A standard abdominoplasty (tummy tuck) works on the front of the abdomen. A Fleur de Lis abdominoplasty adds a vertical excision to treat horizontal laxity but stops at the flanks. A body lift (belt lipectomy) treats the full circumference but leaves horizontal excess at the front untouched.
The circumferential hybrid abdominoplasty is a technique I developed and named in my practice to treat this combined pattern in a single operation. It is a body lift (belt lipectomy) combined with a vertical midline excision on the front of the abdomen, designed to remove excess skin in both directions across the abdomen while also treating the flanks, lower back, and buttock region.
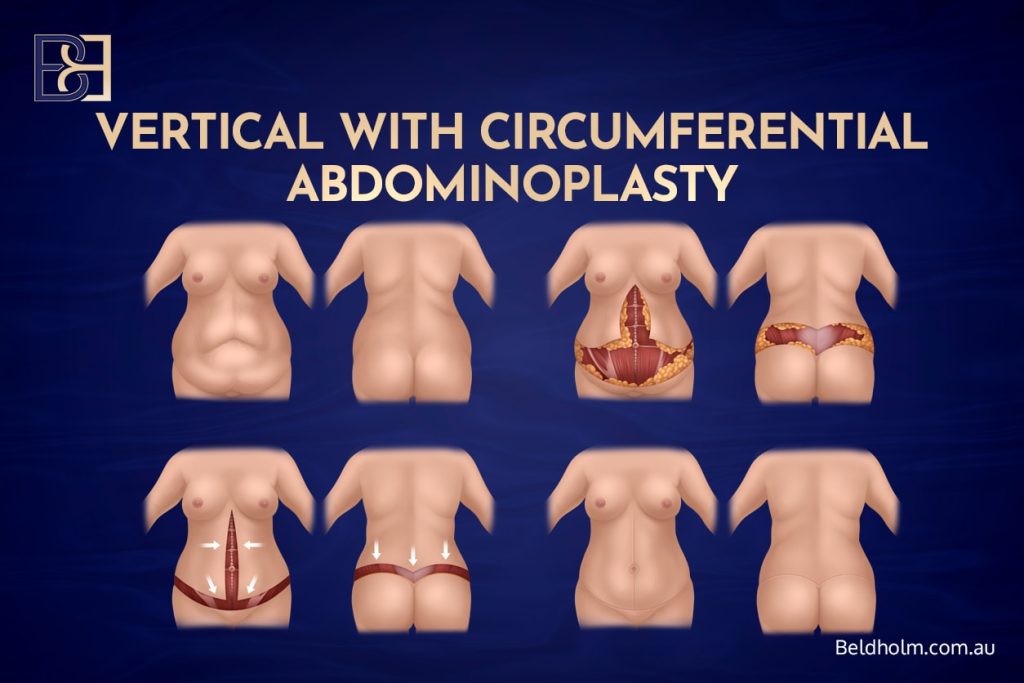
This article explains what the operation involves, how it differs from a circumferential abdominoplasty on its own, who it may suit, how I decide between one larger operation and staged surgery, and what to expect across the surgery and recovery process, including preparation, hospital stay, scars, and cost. Recovery and complications each have their own detailed articles, which I link to below.
What Is a Circumferential Hybrid Abdominoplasty?
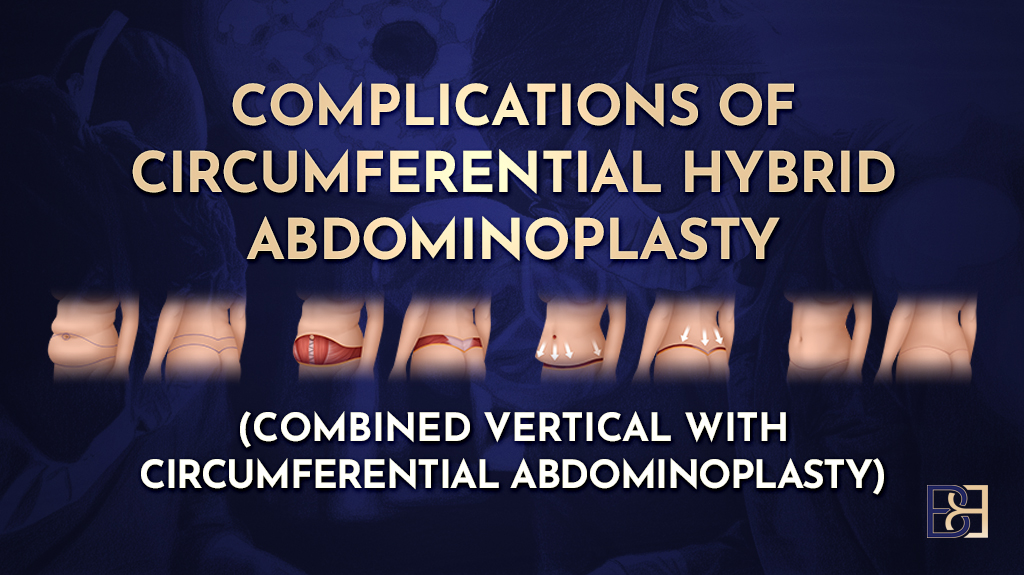
A circumferential hybrid abdominoplasty is a surgical procedure that combines a body lift (belt lipectomy) with a vertical midline excision at the front of the abdomen, performed as one operation. In technical terms, it is a circumferential hybrid abdominoplasty combining a vertical lipectomy with belt lipectomy. I developed this technique for post weight loss patients whose skin excess runs in multiple directions and continues around the trunk.
The operation has 2 components:
- The circumferential component. A transverse excision that runs around the entire lower torso, the same excision used in a body lift (belt lipectomy). This removes vertical skin excess from the abdomen, flanks, lower back, and buttock region, and lifts the buttocks and outer thighs.
- The vertical component. A midline excision at the front of the abdomen, the vertical limb used in a Fleur de Lis abdominoplasty. This removes horizontal skin excess, the side to side laxity that a transverse excision cannot treat.
Combined, the 2 excisions treat skin excess in both directions across the front of the abdomen while also treating the full circumference of the lower torso.
What the operation can include
Depending on what I find at assessment, the operation may also involve:
- Repair of muscle separation (diastasis recti) where present, tightening the underlying muscles. This is not routine in post weight loss patients
- Repair of hernias found at assessment or during surgery
- Reconstruction of the belly button (umbilicus)
- Lifting of the mons
- Removal of existing scars that sit within the excision, such as caesarean or appendix scars
- Suction assisted lipectomy (liposuction) of adjacent areas in selected patients
Why the trunk is treated as a circle
Weight is not lost from the front of the abdomen alone, so skin excess after massive weight loss rarely stops at the hips, and reduced skin elasticity means the skin cannot shrink back on its own. In my experience, laxity almost always continues past the flanks into the lower back. Treating the torso as a complete circle deals with the whole pattern in one operating time and avoids a result where the front is treated but excess skin folds remain at the sides and back.
This is a major operation, larger than a standard abdominoplasty (tummy tuck) and larger than a body lift (belt lipectomy) on its own. That matters for preparation, operating time, and recovery, which I cover later in this article.
Understanding Skin Excess Patterns After Weight Loss
Choosing the right operation starts with reading the direction of the skin excess. This is the single most useful concept for understanding why the circumferential hybrid abdominoplasty exists.
Vertical excess
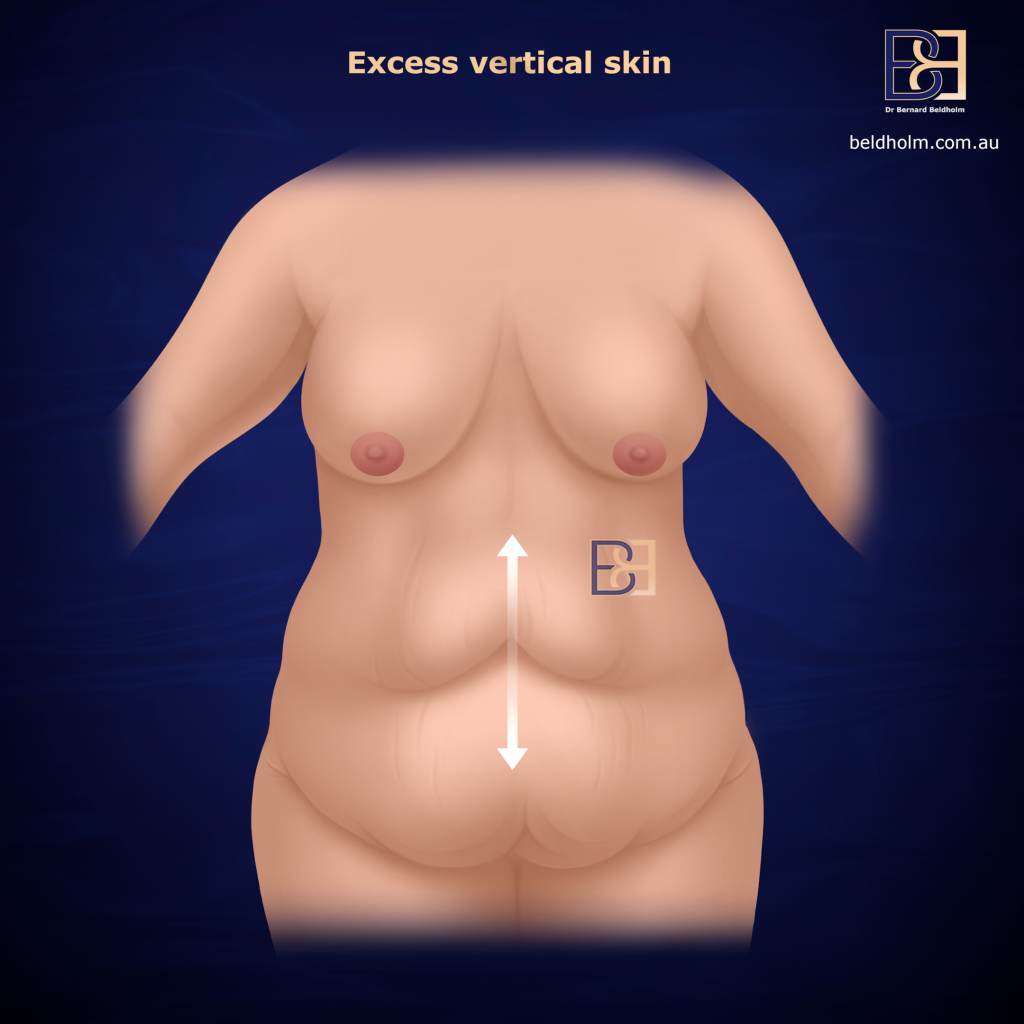
Vertical excess is top to bottom laxity. The skin has stretched lengthwise, and the excess abdominal skin hangs downward, often as an apron over the lower abdomen. To treat it, the excess is gathered and removed through a horizontal excision, a transverse cut low on the abdomen. Pulling the skin down to that excision line takes up the vertical slack. This is what a standard abdominoplasty (tummy tuck) does.
The direction matters: the excision runs perpendicular to the excess it treats. A horizontal excision treats vertical excess.
Horizontal excess
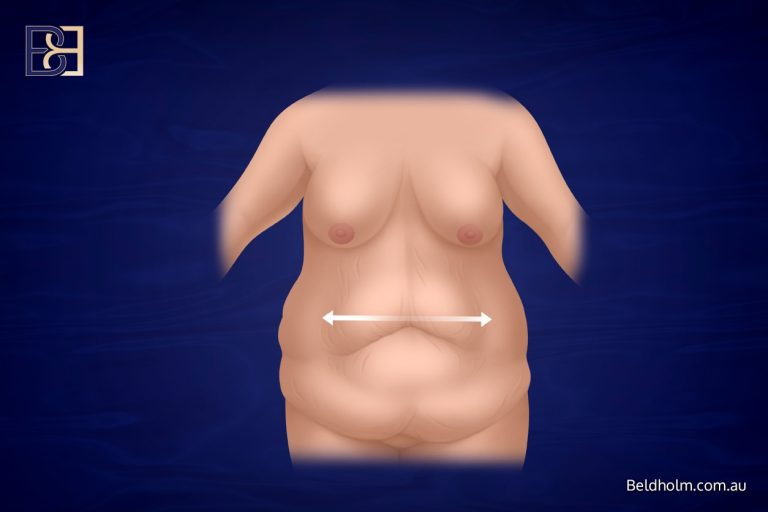
Horizontal excess is side to side laxity. The skin has stretched around the waist, and gathering it downward does not take up that slack. It needs to be gathered toward the midline instead, which requires a vertical excision. This is the vertical limb of a Fleur de Lis abdominoplasty. A vertical excision treats horizontal excess.
Circumferential excess
After significant weight loss, laxity rarely stops at the front. In most of the post weight loss patients I see, the excess continues past the flanks into the lower back and buttock region. A hip to hip excision leaves that lateral and posterior laxity behind, which is why a full abdominoplasty confined to the front of the abdomen is almost never the right operation in this group. Treating the full circle requires the transverse excision to continue around the trunk, which is the body lift (belt lipectomy).
The combined pattern
Many post weight loss patients have all 3 at once: vertical excess at the front, horizontal excess around the waist, and laxity continuing around the trunk. That combined pattern is what the circumferential hybrid abdominoplasty treats. The circumferential excision deals with the vertical excess around the entire trunk, and the vertical midline limb deals with the horizontal excess at the front.
At consultation, I map which directions your laxity runs. That pattern, more than any other single factor, determines which operation I recommend.
Circumferential Abdominoplasty vs Circumferential Hybrid Abdominoplasty
Circumferential abdominoplasty, circumferential body lift, lower body lift, and belt lipectomy are different names for the same operation: a transverse excision carried around the entire lower trunk. I cover that operation in detail in my article on belt lipectomy surgery. The question this section answers is when the circumferential operation on its own is enough, and when the hybrid is needed.
What a circumferential abdominoplasty does
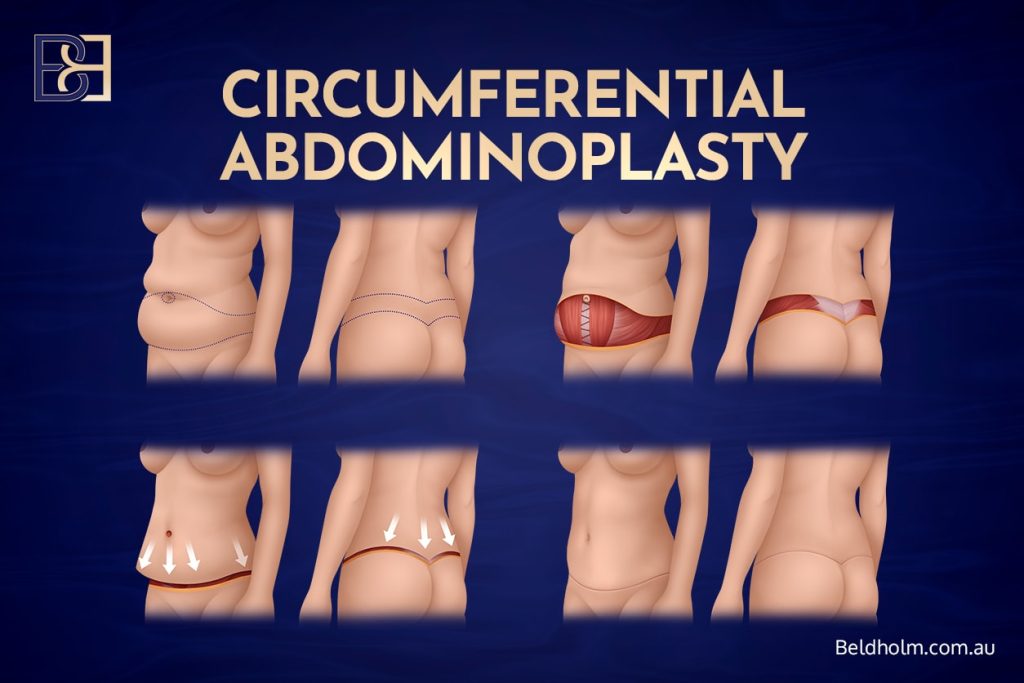
Body lift surgery (belt lipectomy) removes vertical skin excess around the full circle of the lower trunk. At the front, it works like an extended abdominoplasty. At the sides and back, it removes the excess over the flanks and lower back and lifts the buttocks and outer thighs. For a patient whose laxity is predominantly vertical, this comprehensive lower body lift is enough on its own.
What it cannot do
A transverse excision cannot treat horizontal excess. If there is significant side to side laxity at the front of the abdomen, a circumferential abdominoplasty pulls the skin down but leaves that horizontal excess skin behind. The result is a treated trunk with residual redundant skin across the front, most visible around the waist and above the excision line.
What the hybrid adds
The circumferential hybrid abdominoplasty adds the vertical midline excision to the circumferential operation. That vertical limb gathers the horizontal excess toward the midline and removes it, bringing in the waist. Both directions of excess are treated in the same operating time.
The trade-off
The hybrid is not automatically the better choice. It adds a vertical midline scar down the front of the abdomen, which the circumferential operation alone does not have. It also makes an already major operation larger, with longer operating time and greater demand on the body. For a patient without meaningful horizontal excess, the hybrid adds a scar and operative load for no benefit, and the body lift (belt lipectomy) on its own is the right operation.
How I decide
The deciding factor is the pattern I map at consultation:
- Vertical excess extending around the trunk, minimal horizontal excess: body lift (belt lipectomy)
- Vertical and horizontal excess at the front, laxity continuing around the trunk: circumferential hybrid abdominoplasty
- Vertical and horizontal excess confined to the front: Fleur de Lis abdominoplasty
One practical test I use with patients: horizontal excess shows itself when the skin gathers as you pinch it toward the midline rather than downward. If drawing the skin toward the middle of your abdomen takes up the slack, a vertical component is doing work a transverse excision cannot.
How the Techniques Compare
The circumferential hybrid abdominoplasty sits at the end of a spectrum of body contouring procedures for the abdomen. Each step along that spectrum treats a wider pattern of excess. I cover each operation in its own detailed article; this is the short version of where each one fits.
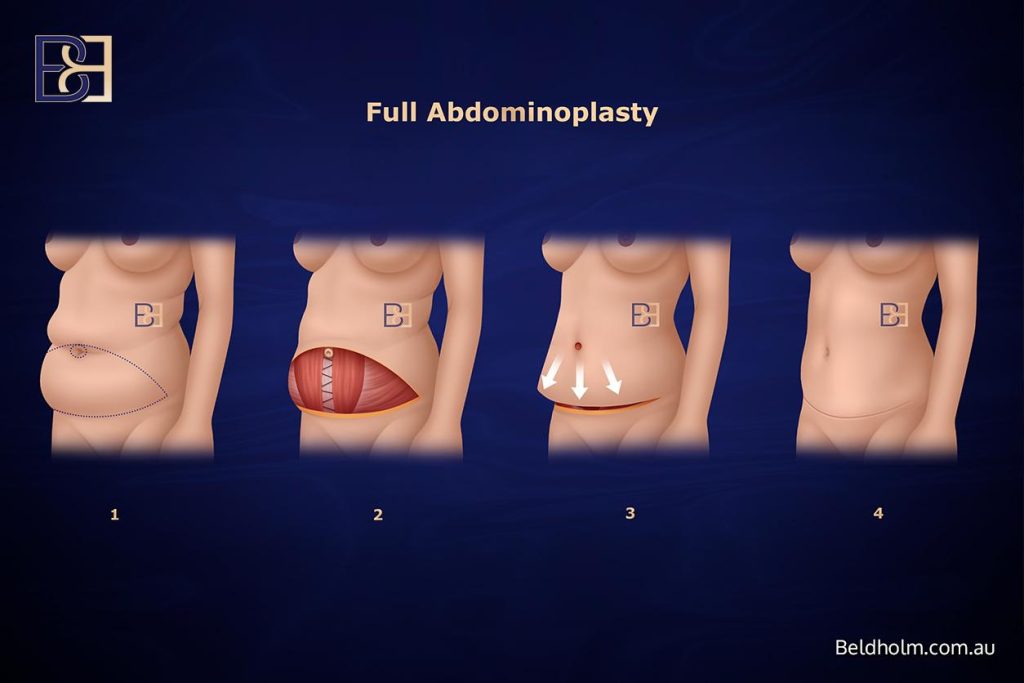
Standard abdominoplasty (tummy tuck). A hip to hip transverse excision at the front. Treats vertical excess on the anterior abdomen. In post weight loss patients I more often perform an extended abdominoplasty, carrying the excision past the hips to treat the flanks, because laxity in this group rarely stops at the front.

Fleur de Lis abdominoplasty. Adds a vertical midline excision to the transverse one. Treats vertical and horizontal excess at the front, but does not treat the lower back or buttock region.
Body lift (belt lipectomy). Carries the transverse excision around the entire trunk. Treats vertical excess circumferentially and lifts the buttocks and outer thighs, but cannot treat horizontal excess at the front.
Circumferential hybrid abdominoplasty. Combines the circumferential excision with the vertical midline limb. Treats vertical and horizontal excess at the front plus the full circumference of the lower torso.
At a glance
Operation | Front: vertical excess | Front: horizontal excess | Flanks | Lower back and buttocks |
|---|---|---|---|---|
Standard abdominoplasty (tummy tuck) | Yes | No | No | No |
Extended abdominoplasty | Yes | No | Yes | No |
Fleur de Lis abdominoplasty | Yes | Yes | Partial | No |
Body lift (belt lipectomy) | Yes | No | Yes | Yes |
Circumferential hybrid abdominoplasty | Yes | Yes | Yes | Yes |
No operation on this table is better than another in the abstract. Each is the right operation for the pattern it matches, and a larger operation than your pattern requires adds scars and operative load without benefit. The full articles on each are linked below:
- Abdominoplasty (tummy tuck) article
- Fleur de Lis abdominoplasty article
- Body lift (belt lipectomy) article
One Operation or Staged Surgery?
The circumferential hybrid abdominoplasty is built on a principle I apply across my post weight loss practice: where a patient is medically suited to it, I prefer to treat their loose skin in a single comprehensive operation rather than dividing the work across several procedures.
The reasoning is practical. One operation means one anaesthetic, one hospital admission, and one recovery period to work through, rather than repeating each of those steps 2 or 3 times. For the lower trunk specifically, it also means the front, flanks, and back are treated together.
This is a preference, not a rule
For some patients, staging the work across separate operations is the more appropriate path. That may be the case when:
- The combined operation would place more demand on the body than is appropriate for that patient
- Medical factors require the work to be spread out
- The extent of the work cannot be completed well in a single operating time
The trade-off
A larger single operation is a bigger physiological event than a smaller one. Longer operating time, more raw surface area healing at once, and a longer recovery. The benefit of consolidating the work is weighed against that greater demand, patient by patient.
This is also why pre-operative preparation carries more weight when a single comprehensive operation is planned, not less. Getting nutritional status and general health right beforehand is part of what makes the larger operation an appropriate choice in the first place. I cover preparation in the next section.
How the decision is made
Whether one operation or staged surgery suits you is a clinical judgement made for you as an individual. It follows assessment of your medical history, nutritional status, the pattern and extent of your skin laxity, and what can be done well in one operating time. It is discussed and decided at consultation, never in advance of meeting you.
Who May Be Suitable
Suitability for a circumferential hybrid abdominoplasty is assessed individually. There is no checklist that decides it in advance, but these are the factors I weigh.
Stable weight. Your weight should be stable for a minimum of 6 months before surgery, and I prefer 12. This applies however the weight was lost: bariatric surgery, weight loss medications, or diet and exercise. Operating while weight is still shifting risks recurrent laxity if weight falls further, or strain on the repair if it rises. The 6 month minimum also aligns with the Medicare criteria I cover later in this article.
The pattern of your skin excess. As covered above, the hybrid suits patients with both vertical and horizontal excess at the front and laxity continuing around the trunk. If your pattern is narrower than that, a smaller operation is the right one.
General health. This is a long operation under general anaesthesia. Heart and lung health, diabetes control, and any history of clotting problems all matter more here than for a smaller procedure. Some medical conditions make staging the more appropriate path; a smaller number make major body contouring surgery inadvisable altogether.
Nutritional status. Most post weight loss patients have nutritional gaps, and a larger operation gives the body more healing to do. I assess this formally with blood tests before surgery, covered in the next section.
Smoking and nicotine. Nicotine constricts the small blood vessels the skin relies on to heal. With a circumferential wound plus a vertical limb, that matters. I require patients to stop smoking, vaping, and all nicotine replacement well before surgery.
Body mass index. I use BMI as a rough guide only, not a hard cut-off. A higher BMI raises the risk of wound complications and clotting problems, and I discuss that with you directly, but the decision rests on your overall clinical picture rather than a single number. DEXA scans are not part of my routine assessment.
A GP referral is required before consultation. It also means your GP is involved from the start, which matters for a procedure with this much preparation and follow-up.
Preparing for Surgery
Because this is one of the larger operations I perform, preparation carries more weight than it would for a smaller procedure. The work done in the months before surgery supports the healing your body has to do afterwards.
Pre-operative blood tests
Every post weight loss patient in my practice has a full pre-operative blood panel. Significant weight loss, whether through bariatric surgery or weight loss medications, commonly leaves nutritional gaps that show up in blood work rather than in how you feel. The panel covers blood count, clotting, liver and kidney function, glucose control, iron studies, thyroid function, and a broad set of vitamins and minerals including vitamins A, B1, B6, B12, folate, vitamin D, vitamin E, zinc, and selenium.
I go through the panel and what each result means for surgery in my article on pre-operative blood tests.
Nutritional preparation

Where the blood work shows gaps, I correct them before surgery. Protein matters most: skin removal surgery creates long wounds, and wound healing is protein demand. Alongside protein, the common gaps in this group are iron, vitamin D, B12, and zinc, each of which has a role in healing or oxygen delivery.
I have written separately about protein intake after weight loss and the common nutritional deficiencies I see in post weight loss patients, including how each is corrected. Rather than repeat that here, follow those articles if you want the detail. The principle for this operation is: the bigger the operation, the more the preparation matters.
Blood clot risk assessment
A long operation on the trunk carries a higher risk of deep vein thrombosis than shorter procedures. I stratify every patient’s clotting risk before surgery and decide the prevention plan myself, as the operating surgeon. That plan spans compression, early walking, and, where indicated, blood thinning medication after surgery.
Medications before surgery

Aspirin and anticoagulants are typically stopped 1 week before surgery, but this is planned individually and well in advance. Some patients need to continue through surgery. Do not stop any medication on your own; tell me everything you take and I will give you a written plan.
For patients on weight loss medications, current Australian guidelines do not recommend routinely stopping them before surgery, and I follow that guidance. If protein targets cannot be met while on the medication, a temporary dose adjustment may be discussed as part of your individual plan. This is a decision made with me, never on your own.
The anaesthetic consultation

The majority of anaesthetic consultations for my patients happen by phone before surgery. The physical examination, including airway assessment, happens on the day of surgery. An in-person pre-operative anaesthetic review is rarely needed.
What Happens During the Operation
Knowing the sequence helps the operation make sense, so here is how the day runs.
Marking and anaesthesia
I mark the incision lines with you in the anaesthetic bay before surgery, standing and lying, so the excision matches how your skin actually sits. The operation is performed under general anaesthesia at Maitland Private Hospital, and it is one of the longer operations I perform.
The back first
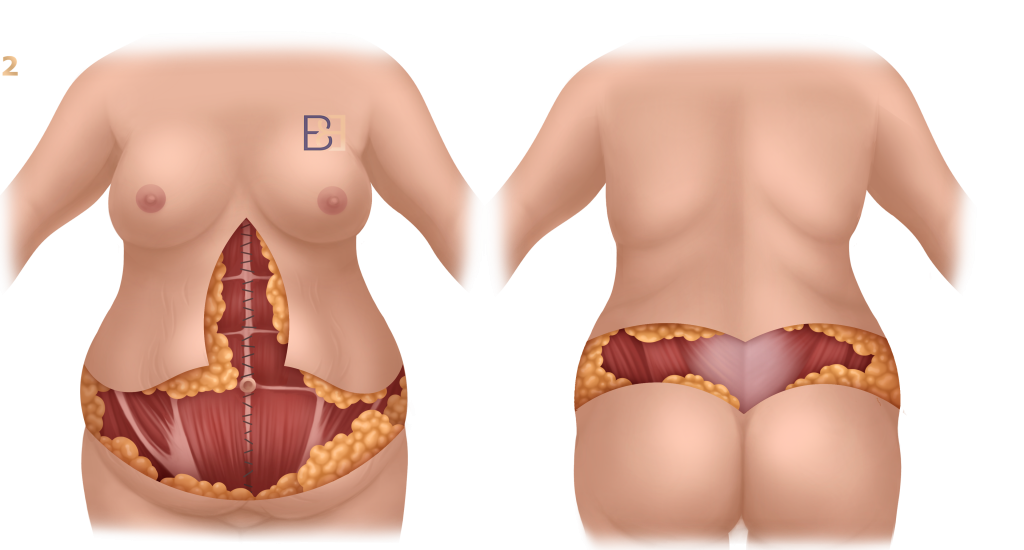
The operation is staged on the table. You are positioned face down and I complete the posterior part first: the excision across the lower back, lifting the buttock region and outer thighs, and closing that part of the wound. Completing the back first means that when you are turned over, the front can be closed without pulling against a fresh posterior repair, and the repair at the front is not strained by the turn.
Then the front
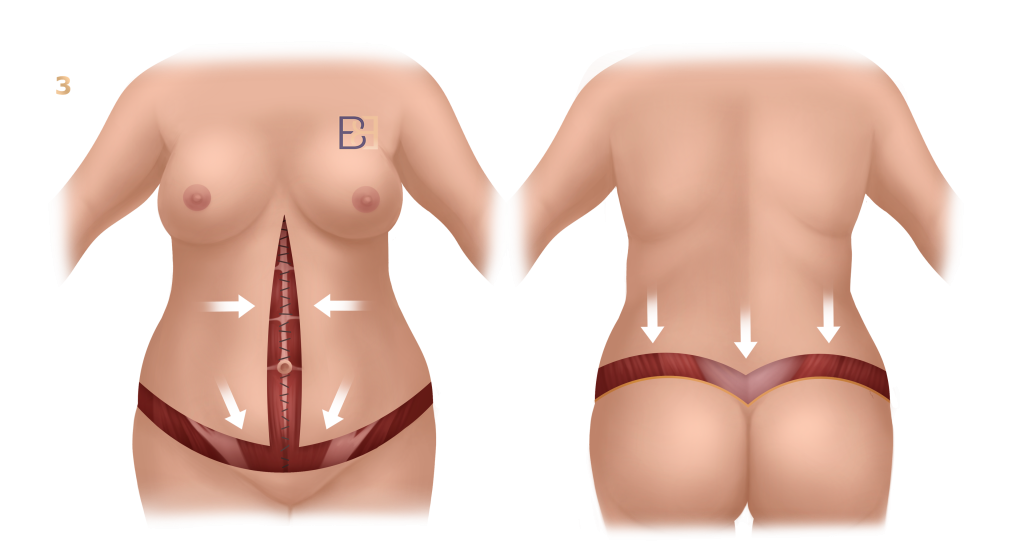
You are turned onto your back and the anterior stage begins. This combines the front of the body lift (belt lipectomy) with the vertical midline excision:
- The transverse excision is carried across the lower abdomen, removing excess skin and fat and connecting with the posterior excision at each flank
- The vertical midline excision removes the horizontal excess, drawing the waist inward and reshaping the abdominal contour
- Muscle separation (diastasis recti), where present, is repaired, bringing the underlying abdominal muscles back together at the midline of the abdominal wall
- Hernias found at assessment or during surgery are repaired
- The mons is lifted
- The belly button (umbilicus) is reconstructed in its new position
- Existing scars that sit within the excision, such as caesarean scars, are removed with the tissue
In selected patients, suction assisted lipectomy (liposuction) of adjacent areas is added, decided beforehand as part of the surgical plan.
Closure, drains, and dressings
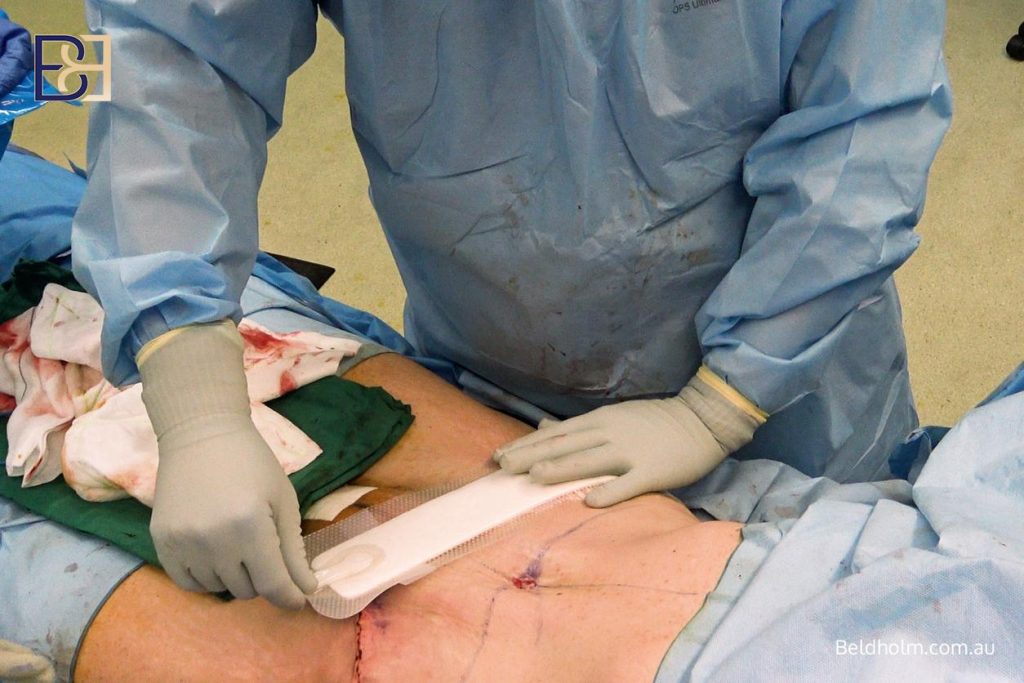
The wounds are closed in layers with dissolving sutures. I place 2 closed suction drains, 1 at each hip, to remove fluid from the space under the skin while it heals. Before you leave theatre, PICO negative pressure dressings are applied to the incisions at the front, both the transverse and the vertical midline, and the posterior incision is covered with Comfeel dressings. A compression garment is fitted over the top.
The result is a scar that runs around the lower torso, sitting low enough to be covered by underwear, plus a vertical midline scar at the front. I cover scars in more detail later in this article.
Hospital Stay and Early Recovery

I have written a full article on recovery after a circumferential hybrid abdominoplasty, covering the complete timeline week by week. This is the short version.
The initial recovery period begins in hospital. You stay at Maitland Private Hospital after surgery, usually 2 to 3 nights. How long is a clinical decision I make day by day based on how you are recovering. You are up and walking on day 1, bent slightly forward to protect the repair at the front, and you use a spirometer to keep your lungs expanded. The most common issue I manage in the first days is blood pressure, and the nursing team monitors this closely. You receive blood thinning injections in hospital, and most patients continue them for about 2 weeks at home. A dietitian is available on the ward if protein intake or nutrition becomes an issue during your stay, and a range of protein supplements is stocked. You are welcome to bring your own whey protein isolate.

Some patients go home with 1 or both drains still in place. That is routine, and my team teaches you drain management and wound care before discharge. The PICO dressings on the front incisions stay on until about day 7, after which the wounds are dressed with Hypafix tape. Compression garments are worn full time for about 4 weeks, then part time for a further 2 weeks.
The recovery process is longer and more demanding than recovery from a standard tummy tuck abdominoplasty. There is a wound running the full circle of your torso plus a vertical wound at the front, and sitting, standing, and lying all load some part of it. In the early recovery period, avoid heavy lifting, plan for time off work, and arrange help at home.
For the full timeline, including movement, showering, driving, return to work, and garment weaning, read the recovery article.

Risks and Complications
I have written a dedicated article on complications of circumferential hybrid abdominoplasty, covering each risk, how often problems occur, and how I manage them. Read it before deciding on surgery. The headline risks are below.
This is major surgery, and it carries more risk than a standard abdominoplasty (tummy tuck) because the wound is longer, the operation takes more time, and the body has more healing to do. The risks that matter most:
- Wound healing problems. The most common complication group. The points where the vertical and transverse incisions meet carry the highest tension, and small areas of wound breakdown or delayed healing can occur there
- Seroma. Fluid accumulation under the skin after the drains come out, sometimes needing drainage in the rooms
- Blood clots (deep vein thrombosis and pulmonary embolism). A longer operation on the trunk raises this risk, which is why risk stratification, blood thinning injections, and early walking are built into my protocol
- Bleeding, haematoma, and infection. As with any major surgery
- Scar concerns and asymmetry. Some patients need a revision procedure once healing is complete
None of these risks is a reason to avoid surgery on its own. They are the reason careful patient selection, preparation, and follow-up are structured the way they are in my practice. The complications article covers all of it in detail.

Scars and Long Term Considerations
This operation trades loose skin for scars. That trade should be understood clearly before you decide, because the scars are permanent.
Where the scars sit
There are 2 scar lines:
- A circumferential scar running around the entire lower torso. I plan it to sit low, within the line of underwear or swimwear where possible
- A vertical midline scar running up the front of the abdomen from the transverse scar. Unlike the circumferential scar, this one is visible when the abdomen is uncovered
The vertical scar is the price of treating horizontal excess. Patients who choose this operation are generally trading a visible midline scar for the removal of skin excess that no other single operation can treat. In my experience, patients who have carried significant loose skin make that trade with their eyes open, but it has to be your decision, made with a clear picture of what the scars look like.
How scars mature
Scars are at their most raised and red between roughly 6 weeks and 3 months, then settle as the healing process continues over 12 to 24 months, fading and flattening. Scar maturation differs between patients, and results vary. Silicone therapy, taping, and sun protection all help, and I guide this through your follow-up visits at 4 weeks, 3 months, 6 months, and 12 months.
Keeping the result
The operation removes skin; it does not hold your weight stable. Significant weight gain stretches the remaining skin, and significant further loss can create new laxity. Weight stability, supported by a healthy lifestyle, is what protects the result long term, which is another reason I want weight stable well before surgery rather than still moving.
Medicare and Cost

A circumferential hybrid abdominoplasty may attract a Medicare rebate when specific criteria are met. The relevant item for circumferential excision of skin after significant weight loss is MBS item 30179. In broad terms, the criteria require that:
- Your weight loss is significant and your weight has been stable for at least 6 months
- The excess skin causes a skin condition, such as intertrigo, where skin irritation develops in the skin folds and has not responded to at least 3 months of non-surgical treatment
- The excess skin interferes with the activities of daily living
Where a Medicare item applies, private health insurance can contribute to hospital costs, depending on your level of cover. Where the criteria are not met, the operation is self funded.
MBS criteria and item numbers change from time to time. Whether an item applies to you is confirmed as part of your assessment, and my rooms will give you a written quote before any decision, covering surgical, anaesthetic, and hospital fees. I explain how the costs are structured in my article on abdominoplasty costs.
Frequently Asked Questions
What is the difference between a circumferential abdominoplasty and a circumferential hybrid abdominoplasty?
A circumferential abdominoplasty, also called a body lift (belt lipectomy), removes vertical skin excess around the entire lower torso through a transverse excision. A circumferential hybrid abdominoplasty adds a vertical midline excision at the front, which also removes horizontal skin excess. The hybrid is a technique I developed for patients whose laxity runs in both directions and continues around the trunk. Patients sometimes describe it as a hybrid tummy tuck abdominoplasty.
How is it different from a Fleur de Lis abdominoplasty?
A Fleur de Lis abdominoplasty uses the same 2 excisions at the front, transverse plus vertical, but stops at the flanks. The hybrid carries the transverse excision around the entire trunk, treating the lower back and lifting the buttock region as well.
Can other procedures be combined with it?
Sometimes. Whether work such as brachioplasty (arm lift), thighplasty (thigh lift), mastopexy (breast lift), or breast reduction is done in the same operation or staged separately depends on operating time, the load the combined surgery would place on your body, and your medical picture. For some patients staging is the more appropriate path. This is assessed individually at consultation.
How long is the hospital stay?
Usually 2 to 3 nights at Maitland Private Hospital. How long you stay is a clinical decision made day by day based on your recovery.
Where do the scars sit?
One scar runs around the lower torso, planned to sit within the line of underwear where possible. The second runs vertically up the midline of the front of the abdomen and is visible when the abdomen is uncovered. Both are permanent and mature over 12 to 24 months.
Will Medicare cover it?
A rebate may apply under MBS item 30179 when the criteria are met, including 6 months of stable weight, a skin condition that has not responded to non-surgical treatment, and interference with daily activities. Whether the item applies to you is confirmed at assessment. MBS criteria change from time to time.
Final Thoughts

The circumferential hybrid abdominoplasty exists because post weight loss skin excess often refuses to follow a single direction. For patients with vertical and horizontal excess at the front and laxity continuing around the trunk, it treats the whole pattern in one comprehensive body contouring operation: one anaesthetic, one admission, one recovery.
It is also one of the larger operations I perform, and that cuts both ways. Consolidating the work is a genuine benefit for a patient who is suited to it, and a larger operation places greater demand on the body, which is why preparation, patient selection, and structured follow-up carry the weight they do in my practice. For some patients, staging the work is the more appropriate path.