Losing a large amount of weight is a major achievement, whether you reached your goal through diet and exercise, weight loss medication, or bariatric surgery. For many of the people I see in my practice, that achievement comes with a frustrating physical reality. Once the weight is gone, the skin that stretched to accommodate it often does not shrink back. You are left with loose, hanging skin across the abdomen that no amount of further dieting or training will tighten.

An abdominoplasty (tummy tuck) removes this excess skin and reshapes the abdomen once your weight has settled. Body contouring surgery for people who have lost significant weight makes up a large part of my work, and this guide reflects what I see and do for these patients.
Why a guide written for post weight loss patients?
Most general information about tummy tuck surgery (abdominoplasty) is written with the post-pregnancy patient in mind. The post weight loss abdomen is different, and the surgery has to account for that.
After pregnancy, the main problem is often separated abdominal muscles (diastasis recti) with a relatively modest amount of loose skin. After major weight loss, the picture is usually the reverse. There is a large volume of loose skin, the laxity frequently extends around the flanks and lower back, and the belly button (umbilicus) is commonly stretched and pulled downward. Many post weight loss patients do not have significant muscle separation (diastasis recti) at all. Planning the operation around the post-pregnancy model misses what these patients actually need.
This guide covers who is suited to surgery, the operations I use, how I decide between 1 comprehensive operation and staged surgery, preparation, the operation itself, and an overview of recovery, risks, and cost, with links to my detailed articles on each of those topics.
The Post Weight Loss Abdomen and How It Presents
When a post weight loss patient comes to see me, the weight has usually already gone. The problem that remains is the skin. Understanding how the abdomen presents after major weight loss explains why the surgery is planned the way it is.
Loose, overhanging skin

The most common finding is a large amount of loose skin across the lower abdomen, often hanging as an apron over the pubic area and upper thighs. Skin has a limited ability to shrink back after it has been stretched for a long time. Whether weight is lost gradually or through rapid weight loss, and especially after massive weight loss, skin elasticity is reduced and the skin does not retract to fit the smaller frame underneath.
This is not something further weight loss, creams, or exercise can fix. Once the skin has lost its elastic recoil, surgery to remove excess skin is the only reliable way to deal with it.
The belly button (umbilicus)
In post weight loss patients the belly button (umbilicus) is usually stretched and pulled downward, sitting lower than it should and elongated by the weight of the overhanging skin. It is one of the reasons a standard post-pregnancy approach does not translate directly to these patients, and it shapes how the belly button (umbilicus) is handled during surgery.
Where the laxity extends

Loose skin after major weight loss rarely stays neatly on the front of the abdomen. It commonly continues around the flanks and into the lower back, and the mons pubis is frequently involved as well. The pattern is often closer to a circumferential one than a front-of-abdomen problem alone. Assessing how far the laxity extends is a key part of working out which operation fits, and it is the reason the extended and circumferential operations feature so heavily in my post weight loss work.
Muscle separation (diastasis recti) is not the usual driver
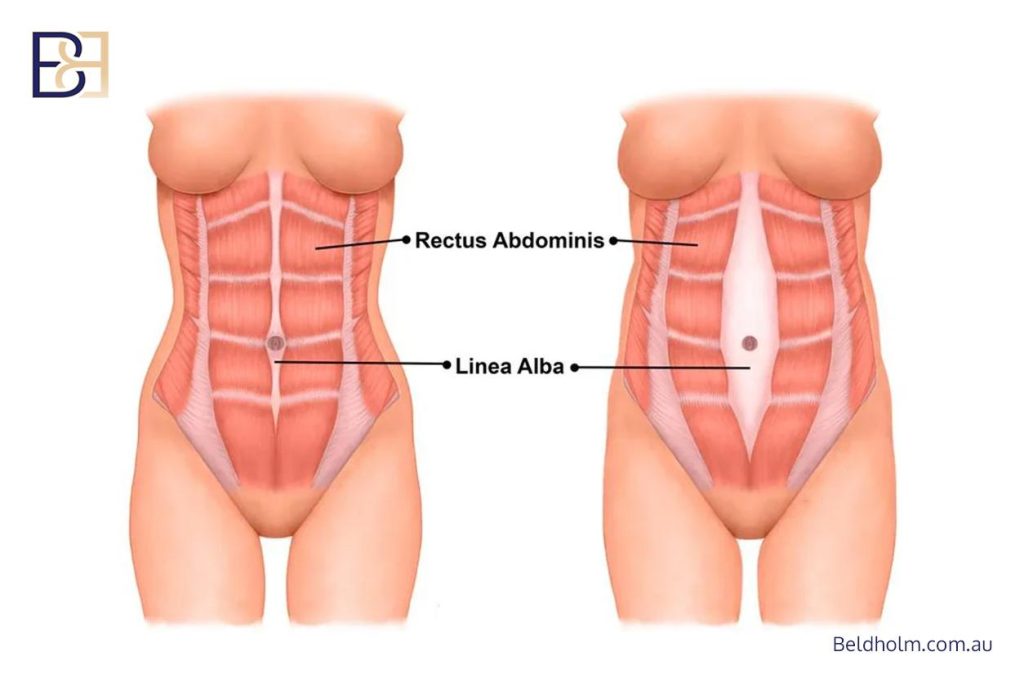
Separated abdominal muscles are mainly a post-pregnancy problem, caused by the abdominal wall stretching to accommodate a growing baby. Many post weight loss patients do not have significant muscle separation (diastasis recti) at all. Some do, particularly those who have also been through pregnancy, and where it is present it can be repaired during the operation. Muscle repair is not assumed for these patients the way it often is after pregnancy. Whether the abdominal wall needs anything done to it is assessed for each person individually.
Day to day effects of the excess skin
Beyond appearance, the overhanging skin can cause practical problems. Many patients describe:
- Skin irritation, rashes, and recurrent infection where skin folds rub and trap moisture (intertrigo)
- Difficulty with hygiene in the skin folds
- Trouble finding clothing that fits
- Restriction with exercise and movement
These functional issues are a common reason post weight loss patients look into surgery, not just the look of the abdomen. They also matter when it comes to Medicare eligibility, which I cover later in this guide.
Am I a Candidate for Abdominoplasty After Weight Loss?
Not everyone who has lost weight is ready for surgery straight away. Whether an abdominoplasty (tummy tuck) is the right step depends on a few things I work through with each patient.
Stable weight
The single most important factor is a stable weight. I want patients to be at or near the weight they intend to maintain, and to have held that weight steady for 6 to 12 months before surgery. 6 months is the minimum, and it aligns with the Medicare weight stability criterion. 12 months is preferable.
This matters on both sides. If you are still actively losing weight, more loose skin will develop after the operation, which can compromise the result. If your weight is still fluctuating, the outcome is harder to predict. Surgery works best once the weight loss is complete and settled.
An abdominoplasty (tummy tuck) is not a weight loss operation. It removes loose skin and excess tissue. It is not a substitute for reaching your goal weight first.
General health and fitness
Body contouring surgery after major weight loss is a substantial operation. I assess your overall health, fitness, and any medical conditions to work out whether you are well enough to recover well.
Smoking matters here. Smoking reduces blood supply to healing tissue and raises the risk of wound healing problems. I ask patients to stop well before surgery.
Nutritional readiness

Most post weight loss patients have some nutritional gaps that developed during weight loss, particularly after weight loss surgery (bariatric surgery), and these matter for wound healing. Every post weight loss patient I operate on has a standard pre-operative blood panel to check for these gaps, and I work with the patient, their GP, and a dietitian to put anything right beforehand. How this works is covered in the preparation section later in this guide.
BMI as a guide, not a cut-off
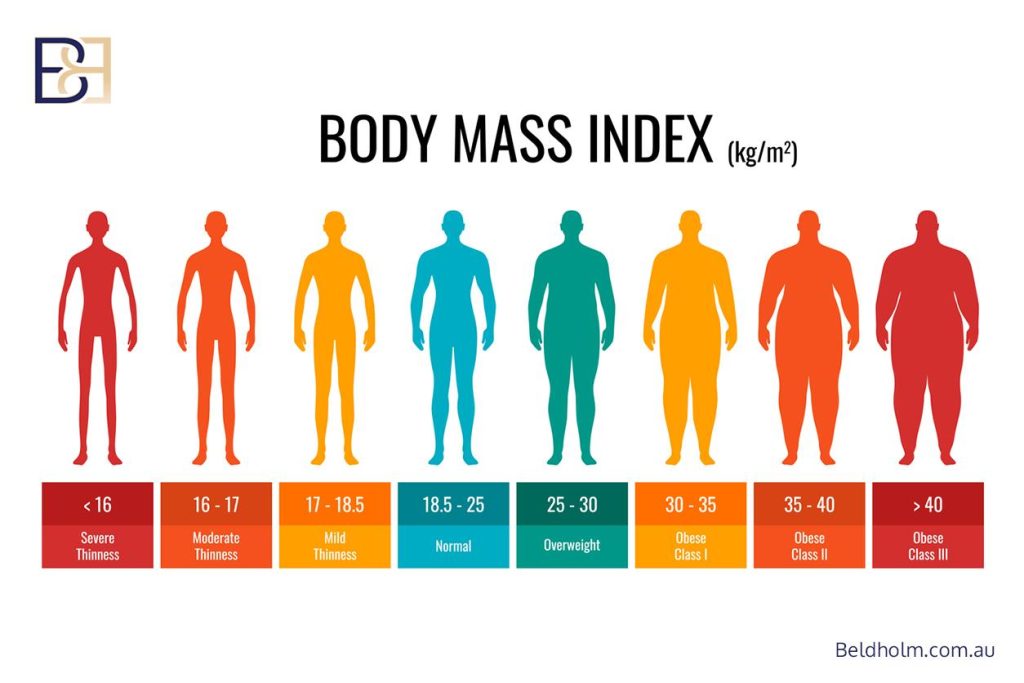
Body mass index (BMI) is a rough guide only. I do not use a hard BMI cut-off, because it does not tell the whole story. Two people with the same BMI can carry their weight very differently and have very different amounts of loose skin. Clinical assessment of your individual situation matters more than a single number. Routine DEXA scans are not part of how I assess candidacy.
Clear expectations
It helps to be clear about what the surgery does and does not do. An abdominoplasty (tummy tuck) removes loose abdominal skin and excess tissue and reshapes the abdominal region. It leaves permanent scars, which I place where they can be covered by underwear or swimwear where possible. It does not remove every contour irregularity, it does not stop future weight change, and it is not a treatment for stretch marks beyond the skin that is removed.
Thinking about future pregnancy

If you are considering future pregnancies, it is important to discuss this during your initial consultation. Pregnancy after an abdominoplasty (tummy tuck) can stretch the repaired tissue again and affect the result, so timing is something to talk through before deciding when to operate.
The Procedure Types I Use After Weight Loss
There is no single tummy tuck (abdominoplasty). The right operation depends on how much loose skin you have and where it sits. Some patients have an overhang limited to the lower abdomen. Others have laxity that runs around the flanks and back, or excess in both the up-and-down and side-to-side directions. Below are the main approaches I use, from less to more extensive. Which one fits is worked out at consultation.
Apronectomy
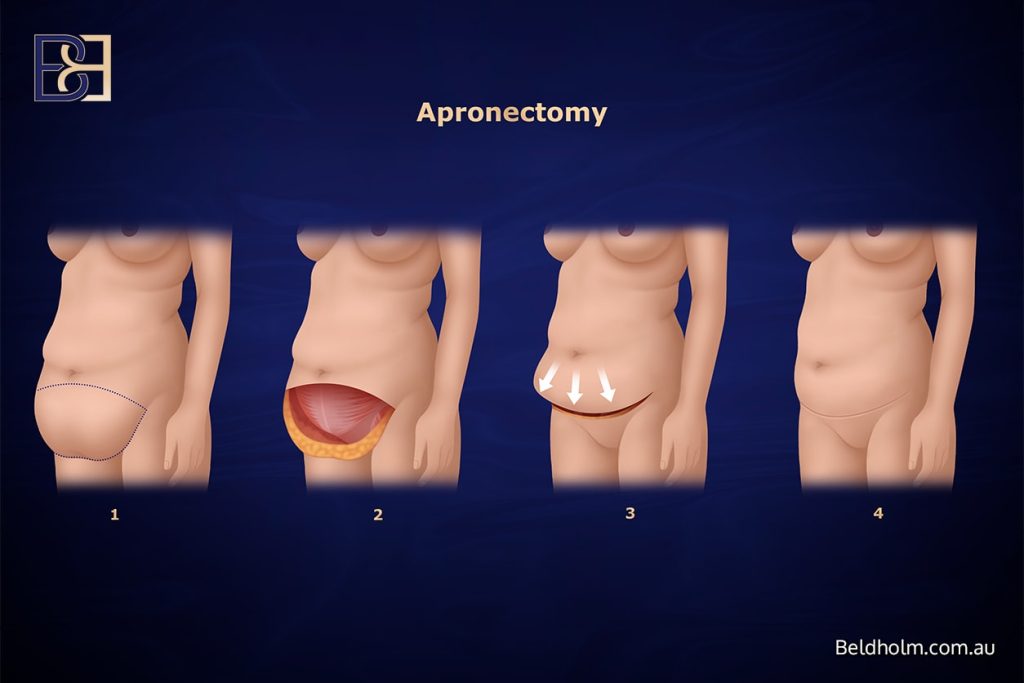
An apronectomy removes the overhanging apron of loose lower abdominal skin, sometimes called a pannus. It is a lower-burden operation. It does not reposition the belly button (umbilicus), tighten the upper abdomen, or do anything to the abdominal wall. It removes the excess skin at the front.
This suits patients whose main problem is a lower abdominal overhang, and patients for whom a longer, more involved operation is not appropriate. For post weight loss patients, an apronectomy is far more relevant than a limited abdominoplasty. A limited abdominoplasty treats only a small amount of lower skin laxity and rarely fits the post weight loss abdomen. I cover this further in my article on apronectomy after weight loss.
Full abdominoplasty (tummy tuck)
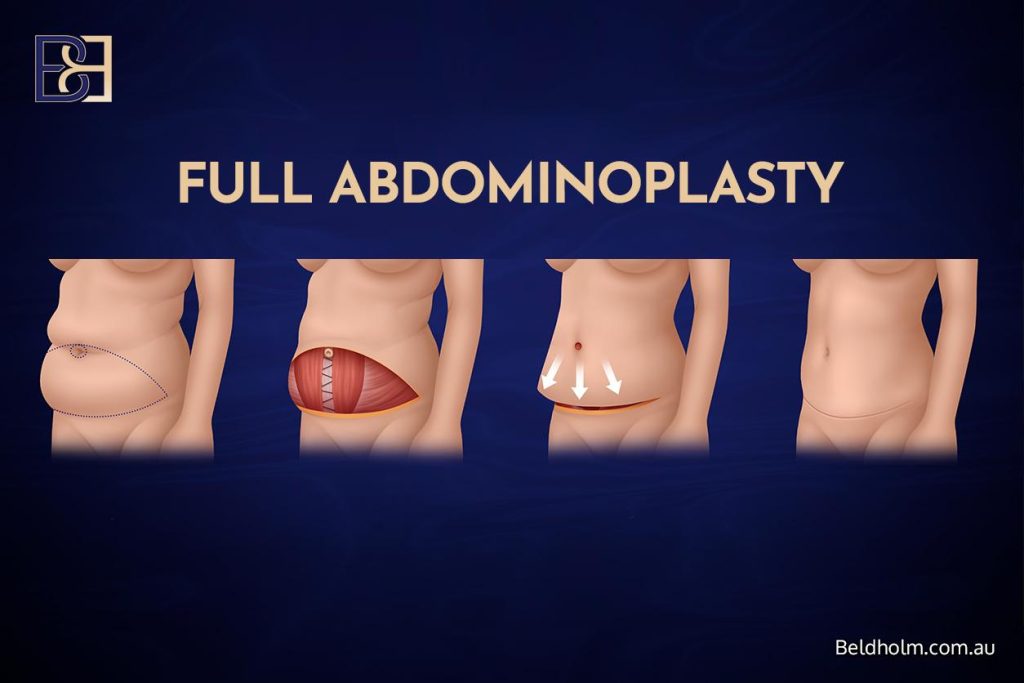
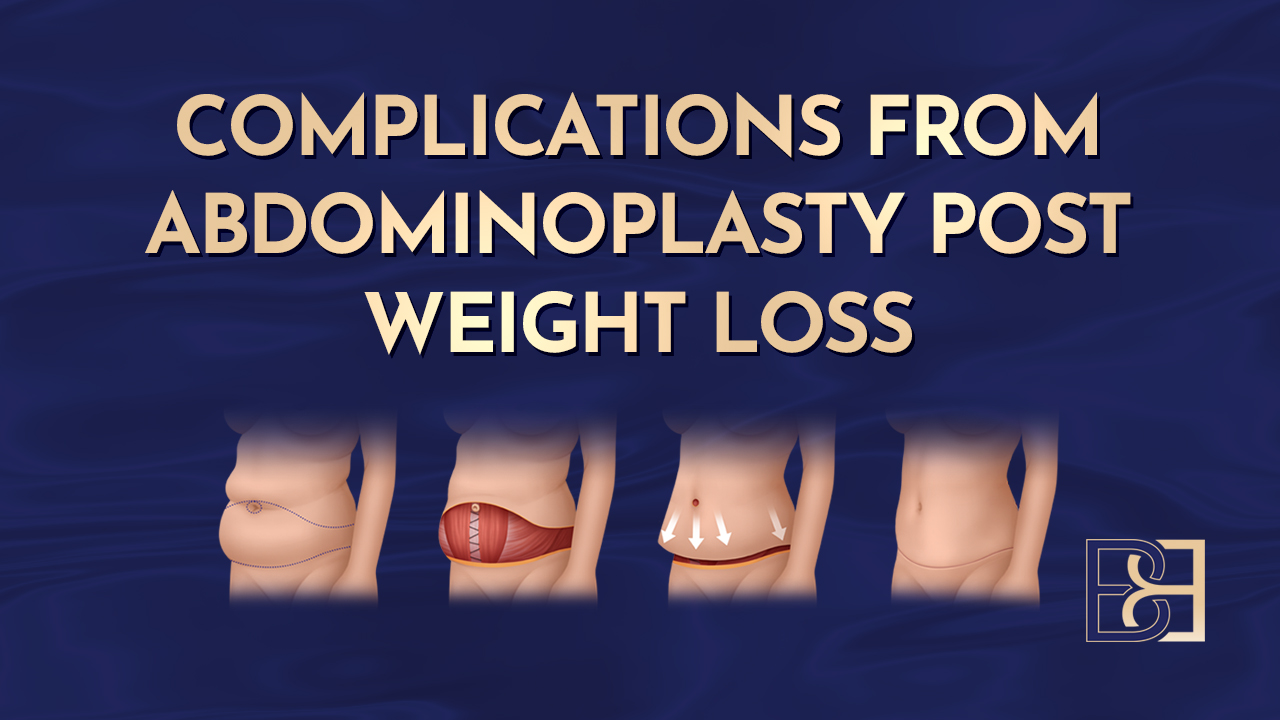
A full abdominoplasty removes excess skin from the lower abdomen, tightens the skin from the rib margin down to the pubic area, and repositions the belly button (umbilicus). The incision runs low across the abdomen from hip to hip. If muscle separation (diastasis recti) is present it can be repaired at the same time.
The full abdominoplasty is the operation most people picture when they think of a tummy tuck (abdominoplasty), and it is the standard approach after pregnancy. In post weight loss patients it has a narrower role. The laxity usually extends past the hips into the flanks, and an incision that stops at the hips leaves that excess behind, which is why the extended version below is my usual anterior operation for this group.
Extended abdominoplasty
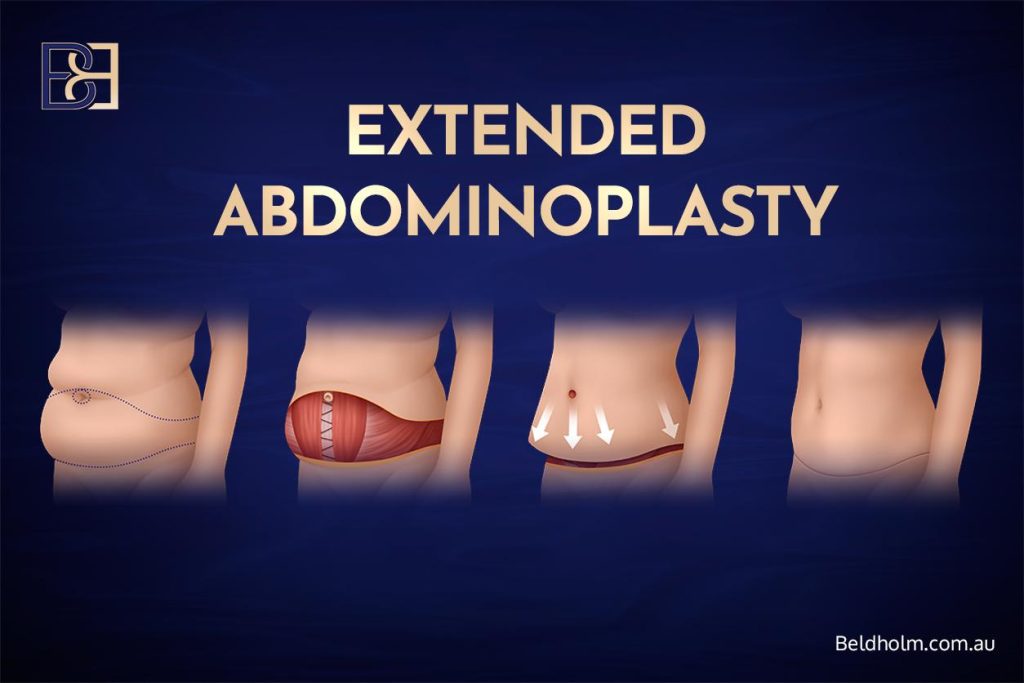
An extended abdominoplasty carries the incision beyond the hips and around towards the back, so the loose skin of the flanks is removed along with the front of the abdomen. Everything else about the operation, including repositioning the belly button (umbilicus), is as described for the full abdominoplasty.
Because loose skin after major weight loss so often continues into the flanks, this is the standard anterior operation for my post weight loss patients. My recovery article covers both the standard and extended abdominoplasty.
Fleur de Lis abdominoplasty
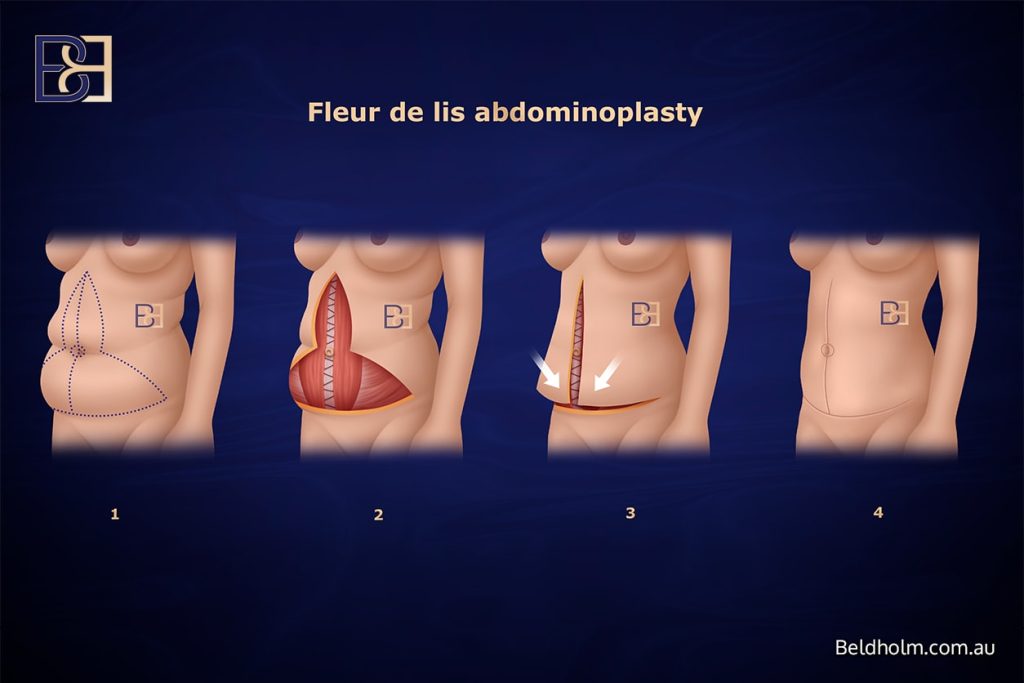
When a patient has a large amount of loose skin in the side-to-side direction as well as up and down, a horizontal removal alone will not deal with it. A Fleur de Lis abdominoplasty adds a vertical incision down the midline of the abdomen, which lets me remove the side-to-side excess and bring in the waistline. The result is a scar in both directions, horizontal across the lower abdomen and vertical up the midline.
This pattern of excess is common after major weight loss. I cover the technique in detail in my article on Fleur de Lis abdominoplasty after weight loss.
Dual vector abdominoplasty
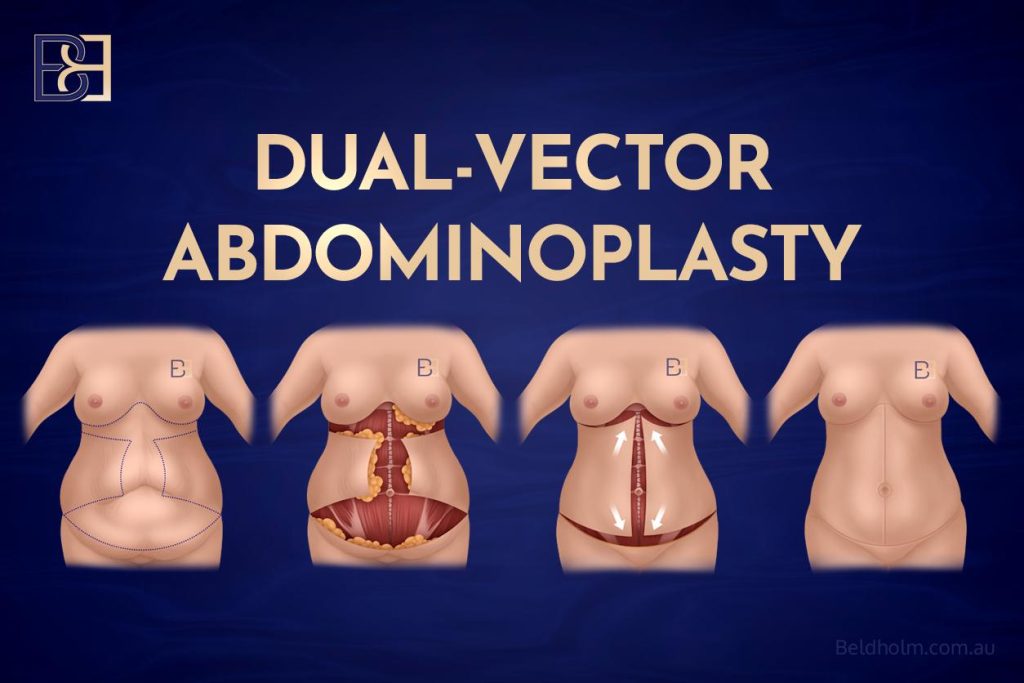
A dual vector abdominoplasty is a technique I have developed for patients who have significant laxity in both the lower and the upper abdomen. It combines a Fleur de Lis abdominoplasty with removal of upper abdominal skin, treating excess in multiple directions that a standard approach would leave behind. It is suited to a particular pattern of laxity rather than being a step up or down from the Fleur de Lis. I explain it further in my dual vector abdominoplasty article.
Body lift (belt lipectomy)

When the loose skin continues around the flanks, lower back, and buttocks rather than staying at the front, the laxity is circumferential and needs to be treated all the way around. A body lift (belt lipectomy) removes a belt of skin around the entire trunk, mainly treating the vertical, up-and-down excess. The same operation is also called a circumferential abdominoplasty or a 360-degree body lift (belt lipectomy). The back portion of the operation lifts the buttock and the outer thigh at the same time. The scar runs around the body, placed low where it can be covered.
I cover this further in my article on body lift (belt lipectomy) after weight loss.
Circumferential hybrid abdominoplasty
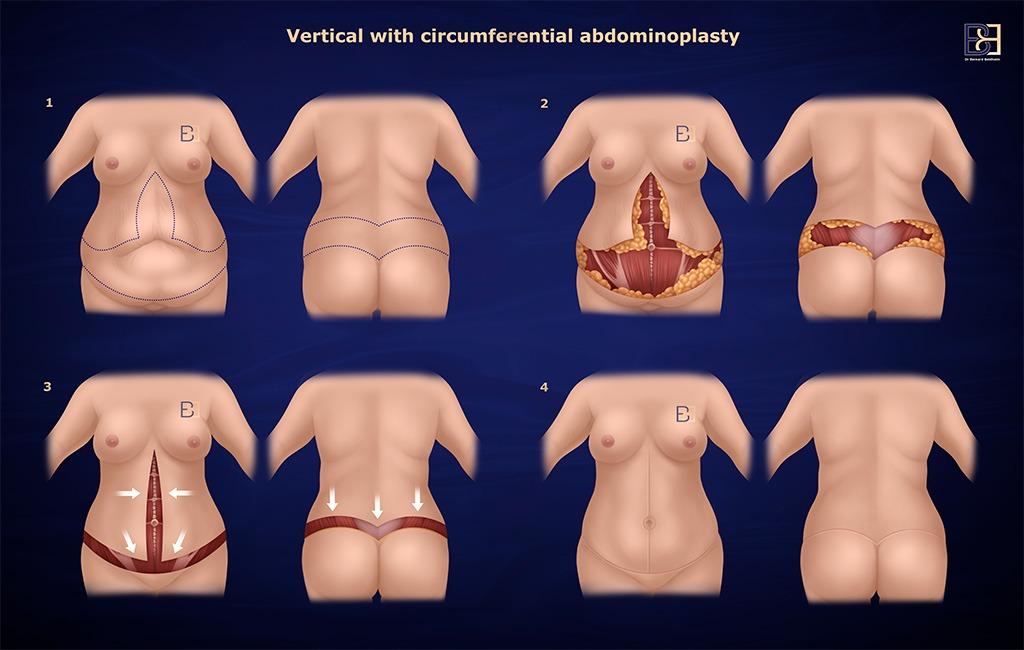
A body lift (belt lipectomy) mainly removes the vertical excess around the trunk. When a patient also has significant side-to-side, horizontal excess across the front of the abdomen, that width is left behind. A circumferential hybrid abdominoplasty is a technique I have developed for this situation. It combines a body lift (belt lipectomy) with an anterior vertical incision that removes the horizontal excess on the front of the abdomen, making it a more complete treatment for loose lower trunk skin. As with a body lift (belt lipectomy), the back portion lifts the buttock and outer thigh. My circumferential hybrid abdominoplasty article covers the operation in full.
Combined suction assisted lipectomy (liposuction)
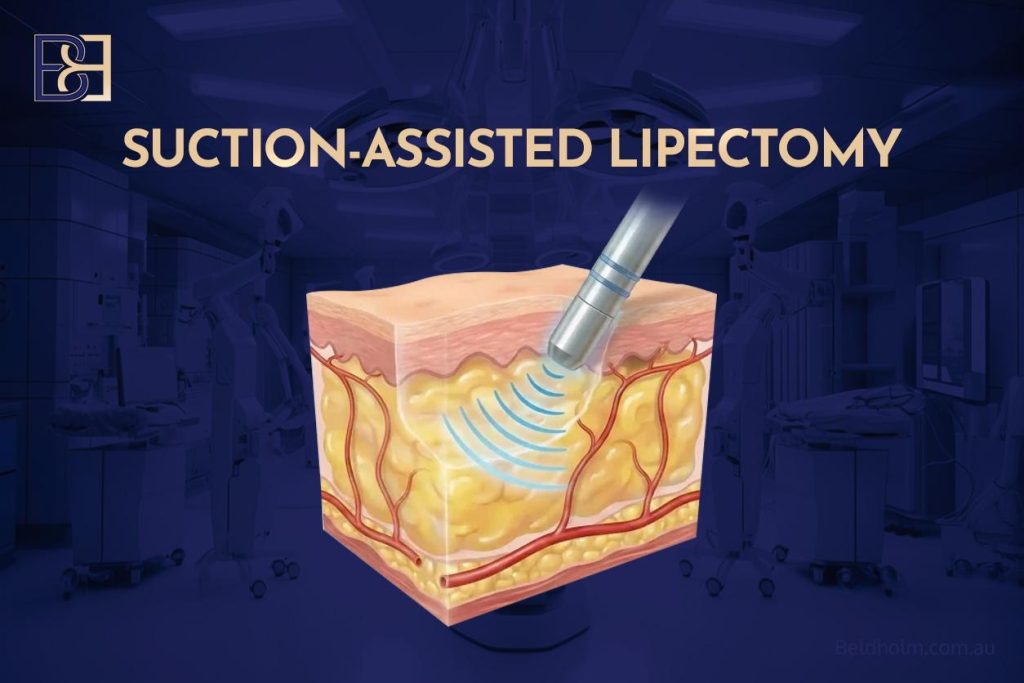
In some patients I use suction assisted lipectomy (liposuction) alongside skin removal to refine the contour of the flanks or upper abdomen. Suction assisted lipectomy (liposuction) removes fat, not loose skin, so it is an adjunct to excess skin removal rather than a treatment for laxity on its own.
Single Comprehensive Operation Versus Staged Surgery
A common question is whether the work can be done in 1 operation or whether it needs to be split into stages. There is no single answer that fits everyone.
My preference, where a patient is suited to it
Where a patient is medically suited to it, I prefer to treat their loose skin in 1 comprehensive operation rather than dividing it across several separate procedures. The reasoning is practical. One operation means one anaesthetic, one hospital admission, and one recovery period to work through, rather than repeating each of those steps 2 or 3 times.
This is a preference, not a rule, and it is never a reason to expand the scope of someone’s surgery beyond what they need.
The trade-off
A larger single operation is a bigger physiological event than a smaller one. A longer operating time places greater demand on the body, and recovery from a comprehensive operation should not be underestimated. This is the trade-off, and it is the reason pre-operative preparation matters more when a single comprehensive operation is planned, not less. Getting that preparation right, covered later in this guide, is part of making the larger operation an appropriate choice in the first place.
When staging is the better path
For some patients, doing everything at once carries more physiological demand than is sensible. In that situation, staging the work across separate operations is the more appropriate path. This can be the case when medical factors require the work to be spread out, or when the extent of the loose skin cannot be treated well in a single operating time.
Staging is a legitimate clinical choice. It is the right approach for some patients, and it is not a lesser option or a compromise.
How the decision is made
Whether 1 operation or staged surgery suits you is a clinical judgement I make with each patient. It follows assessment of your medical history, your nutritional status, the pattern and extent of your loose skin, and what can be done well in a single operating time.
Weight Stability and the Effect of Weight Regain

The result of an abdominoplasty (tummy tuck) is closely tied to your weight, both before and after surgery. This is worth understanding before you decide on timing.
The result is calibrated to your weight at the time of surgery
When I operate, the amount of skin I remove is matched to your frame at that point. The closer you are to a settled, maintainable weight, the more predictable the outcome.
If you go on to lose a significant amount more weight after surgery, the skin that is left can become loose again, because there is now less underneath it. If there is significant weight gain, the skin stretches to accommodate it. Either way, large weight changes after surgery can work against the result. Significant regain can also widen or thicken the scar over time.
Small fluctuations of a few kilograms are normal and not a problem. The concern is large or repeated swings in body weight, which make the long-term outcome harder to hold. This is why I ask patients to be at a weight they can hold before we operate.
Maintaining your result
An abdominoplasty (tummy tuck) removes loose skin. It does not change your weight by much, and it does not prevent future weight gain. Holding onto the result over the years comes down to the same healthy habits that helped you lose the weight in the first place: a balanced diet, regular activity, and a healthy lifestyle. Weight maintenance is what protects the outcome and your body shape.
How an individual heals and how the contour settles depends on several factors, including skin quality, the extent of the loose skin, your weight stability, your nutritional status, and your general health.
Preparing for Surgery
Good preparation is a large part of a good recovery, and it matters more after major weight loss, not less. The work done in the weeks and months before a comprehensive operation counts.
Nutritional optimisation

Most post weight loss patients have nutritional gaps that developed while they were losing weight, and these are more pronounced in post bariatric patients. Low iron, vitamin D, B12, folate, and protein stores are common, and each of these affects wound healing, with gaps raising the risk of poor wound healing. Correcting them before surgery gives the body what it needs to repair afterwards.
Supplementation follows a tiered approach. There is a core set I use for all post weight loss patients, and a second set guided by what your own blood results show. I do not set out the full protocol here, because the blood-guided part depends on your individual results. The detail is in my nutrition articles, including protein after weight loss, nutritional deficiencies after bariatric surgery, and the vitamins and supplements hub. The on-ward dietitian at Maitland Private Hospital is available to review your nutrition if any issues arise around the time of surgery, and your GP looks after the longer term.
The pre-operative blood panel
Every post weight loss body contouring patient I operate on has a comprehensive pre-operative blood panel. It checks full blood count, clotting, liver and kidney function, glucose and HbA1c, thyroid function, iron studies, and a range of vitamins and minerals including vitamin D, B12, folate, vitamin A, vitamin E, zinc, and selenium. Albumin is used as the marker of protein status. Your GP is copied in on these results so the whole team is working from the same information. I go through what each test means in my article on the pre-operative blood panel.
Weight loss medications around surgery
Many of my patients have used weight loss medications. Current Australian perioperative guidance does not recommend routinely stopping these medications before surgery, and I follow that position (1). In some cases, where protein intake targets are difficult to meet, a temporary dose adjustment may be discussed as part of perioperative planning. This is a decision made with you and your treating team. It is not something to adjust on your own.
Medication review and blood thinners
I review all your medications before surgery. Blood-thinning medications such as aspirin and anticoagulants are usually stopped about 1 week before the operation, planned well in advance. Some patients need to continue them through surgery, which is also planned ahead of time. Either way, these medications should never be stopped or changed without instruction.
Anaesthetic assessment
For most patients the anaesthetic consultation happens by phone. The physical examination, including assessment of your airway, is done on the day of surgery. An in-person anaesthetic review before the day of surgery is uncommon.
What Happens During the Operation
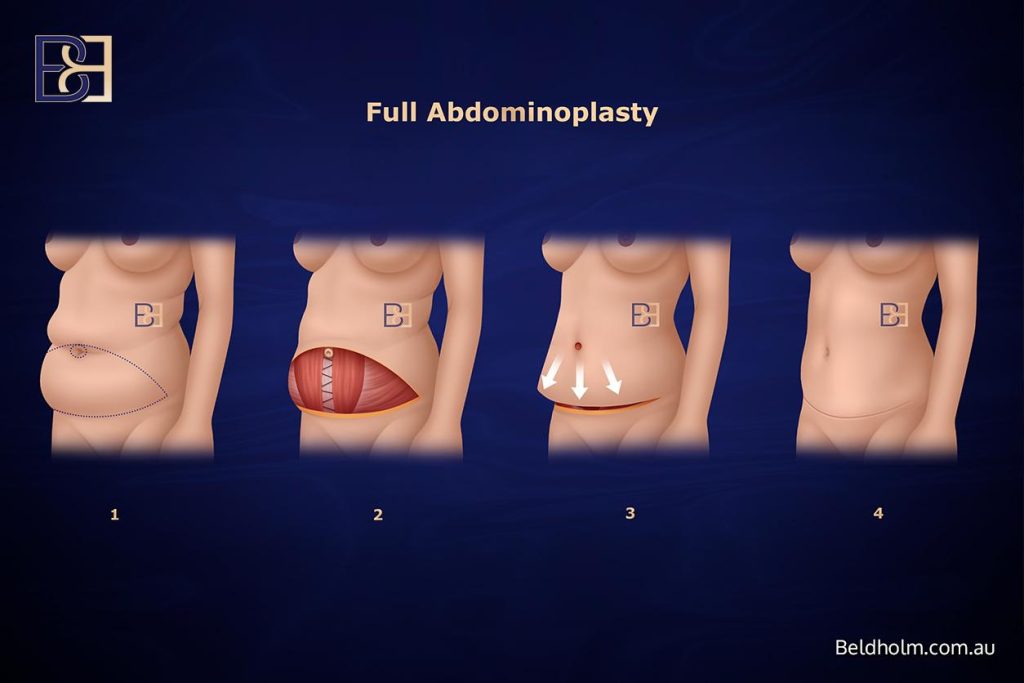
This is a general outline of how the operation runs. The exact steps depend on which abdominoplasty procedure you are having, but the principles below apply across the post weight loss abdominoplasty (tummy tuck) operations I perform. The operation is done under a general anaesthetic.
The incision
For a standard abdominoplasty (tummy tuck) the main incision runs low across the abdomen, placed so it sits below underwear or swimwear where possible. An extended abdominoplasty carries it around towards the back, a Fleur de Lis abdominoplasty adds a vertical incision up the midline, and a body lift (belt lipectomy) continues the incision around the trunk. Where the incision goes is planned and marked before surgery, with you standing, so the skin is removed in the right amount and the right direction.
Lifting the skin and the plane I work in
Once the incision is made, I lift the loose skin and fat off the abdominal wall. I keep the dissection in the plane just deep to Scarpa’s fascia, a strong layer within the fatty tissue. This keeps Scarpa’s fascia inside the skin flap and leaves the deeper fat and the lymphatic channels undisturbed on the abdominal wall. Preserving those lymphatics helps reduce fluid build-up after surgery and supports healing (2).
The belly button (umbilicus)
In post weight loss patients the belly button (umbilicus) is usually stretched and sitting low. The stalk is freed from the surrounding skin, then trimmed and shortened at its base with sutures to treat the stretching. It is then brought out through a new, correctly positioned opening once the loose skin has been removed.
Muscle repair, if needed
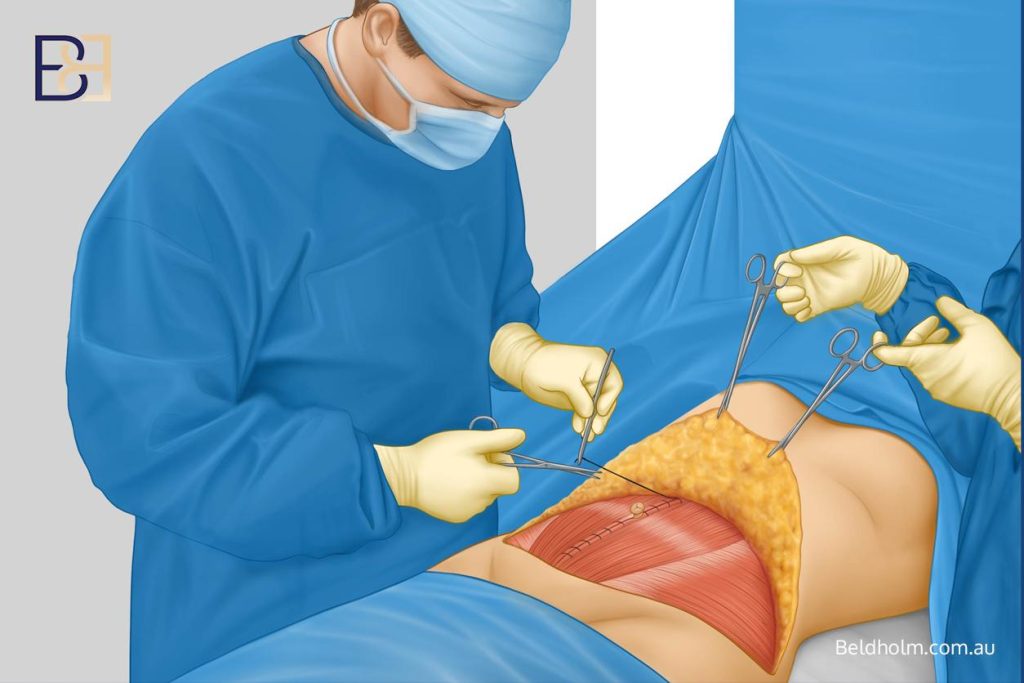
If muscle separation (diastasis recti) is present, the underlying abdominal muscles are brought together and the abdominal wall tightened with sutures at this stage. As covered earlier, many post weight loss patients do not have significant separation and do not need this step.
Removing the excess skin and closing
The excess skin and tissue are removed, and the layers are closed carefully. I repair Scarpa’s fascia as part of the closure, which takes tension off the skin and supports the scar through the healing process.
Drains, dressings, and garment
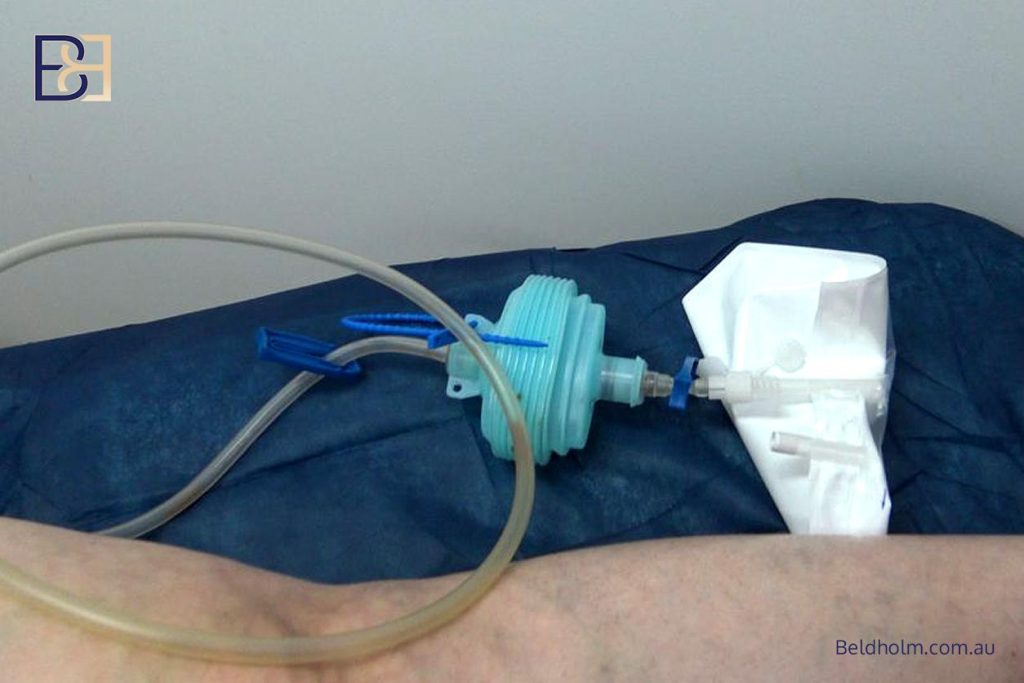
I place 2 closed suction drains, 1 on each side, exiting near the lateral hip. They draw off the fluid that collects after surgery and stay in until the output drops below a set level, usually between 2 and 7 days. I use a drainless technique for some post pregnancy abdominoplasty (tummy tuck) patients, but in post weight loss patients the amount of skin removed is much larger, which leaves a bigger space where fluid can collect, so drains are the better choice here.
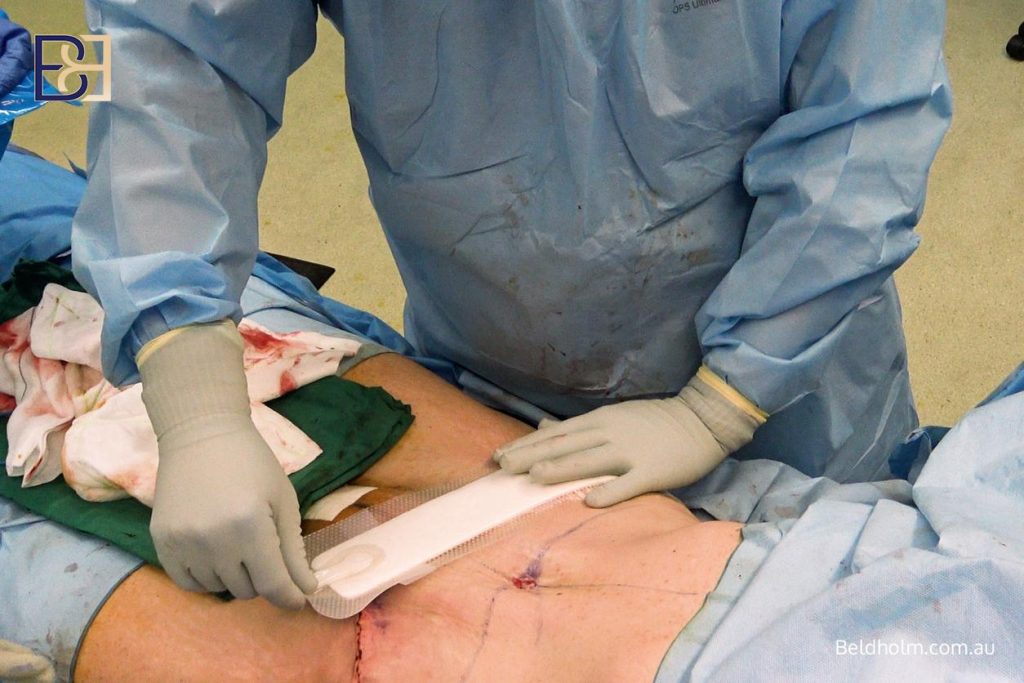
The wounds are covered with PICO negative pressure dressings, changed at around day 7 to a Hypafix tape dressing, and a compression garment is fitted before you wake. How the garment is worn afterwards is covered in the recovery overview below.

Recovery: An Overview

The recovery process runs over weeks and months, not days. A comprehensive operation after weight loss is major surgery and should be given time. I have written a dedicated guide to recovering from abdominoplasty post weight loss, covering the standard and extended abdominoplasty, so what follows is the short version.
Most patients stay in hospital 2 to 4 nights. I want you out of bed and walking on the first day after surgery, because early movement helps your recovery and lowers the risk of blood clots. The drains usually come out between day 2 and day 7, and the PICO dressings are changed to Hypafix tape at around day 7. You wear a compression garment full-time for the first 4 weeks, then half-time for a further 2 weeks, which supports the healing tissues and helps with swelling.

Expect tightness, pulling, and physical discomfort across the abdomen in the first couple of weeks. Pain management in this period is with prescribed pain medications. Swelling builds early and then settles over months, numbness in the lower abdomen is common and usually improves over several months, and the scar softens and fades over 12 months or more.

Plan for around 4 weeks off sedentary work and 6 to 8 weeks off manual or physical work. Many post weight loss patients who have not needed a muscle repair can return to core exercises from around 4 weeks, earlier than after a repair. I review you at 4 weeks, 3 months, 6 months, and 12 months, and at the 4-week visit I hand over to your GP for ongoing care.
The full week-by-week detail, including activity timelines, wound care, and the warning signs to watch for, such as unusual or severe pain, is in my recovery after abdominoplasty post weight loss article.
Risks and Complications: An Overview

Every surgical procedure carries risks, and a larger operation after weight loss carries more of them than a smaller one. You should understand these before you decide. Post weight loss patients also have somewhat higher rates of certain complications, particularly with wound healing, because the wounds are larger and major weight loss changes the body’s nutritional reserves (3). Preparing well reduces these risks but does not remove them.
The main risks are bleeding and haematoma, seroma (a fluid collection under the skin flap, and the reason I use drains in this group), surgical site infection, slow wound healing or wound separation, skin or fat necrosis at the flap edges, blood clots in the leg veins (deep vein thrombosis) with the rare risk of a clot travelling to the lungs, altered sensation in the lower abdomen, asymmetry or contour irregularity, and scars that widen or thicken. Some patients choose a small revision procedure later to refine the result. A general anaesthetic carries its own risks, which your anaesthetist goes through with you.
Blood clot risk deserves particular attention in this group, because longer operations and the post weight loss patient cohort both carry a higher risk. I assess your individual clot risk and decide on the preventive measures myself, rather than leaving it to the anaesthetist. I cover this fully in my article on deep vein thrombosis risk in post weight loss body contouring surgery.
Each of these complications, how often they occur, and how they are managed is covered in my dedicated article on complications from abdominoplasty after weight loss. Before you decide on surgery, I go through the risks that apply to your particular situation, given your health, the procedure planned, and whether the work is done in 1 operation or staged.
Cost, Medicare and Health Insurance

The cost of surgery depends on which operation you have, how complex it is, the length of the operation, the anaesthetic, and your hospital stay. Because these vary from patient to patient, I do not quote a single price here. After your consultation you receive an itemised quote that sets out exactly what is included, and a pricelist is available on this site.
In my practice, most post weight loss patients meet the criteria for a Medicare item number. This applies where the surgery is assessed as reconstructive surgery rather than cosmetic surgery. The item numbers most relevant to this group are MBS 30177, for removal of redundant abdominal skin and fat after significant weight loss with a radical abdominoplasty, and MBS 30179, for circumferential excess treated with a circumferential lipectomy. Broadly, the criteria involve significant weight loss, weight stable for at least 6 months, a skin condition such as intertrigo that has not responded to 3 months of non-surgical treatment, and excess skin that interferes with daily living. The exact criteria are set by the MBS and are subject to revision, so eligibility is assessed against the current wording for each patient and cannot be assumed in advance.
Where a Medicare item number applies, a private health insurance rebate may also be available, depending on your level of cover. Your itemised quote reflects whether an item number applies to your situation. I explain the item numbers, criteria, and documentation in detail in my article on Medicare coverage for post weight loss abdominoplasty.
Frequently Asked Questions

How long should I wait after losing weight before having surgery?
I want you at or near a weight you can maintain, and holding it steady for 6 to 12 months. Operating before your weight has settled makes the result less predictable.
Is an abdominoplasty (tummy tuck) a way to lose weight?
No. It removes loose skin and excess tissue that will not retract after weight loss. It does not change your weight by much and is not a substitute for reaching your goal weight first.
Can I have surgery if I lost the weight through bariatric surgery?
Yes. Many of my post weight loss patients have had bariatric surgery. The main things to sort out first are a stable weight and any nutritional gaps, which is why the pre-operative blood panel matters.
Can I have surgery if I lost the weight with weight loss medications?
Yes. How the weight came off matters less than whether it has settled. Current Australian perioperative guidance does not recommend routinely stopping weight loss medications before surgery, and any adjustment around the operation is planned with you and your treating team, never on your own.
Will I definitely need muscle repair?
Not necessarily. Muscle separation (diastasis recti) is mainly a post-pregnancy issue. Many post weight loss patients do not have it, so muscle repair is not assumed and is only done if you need it.
How visible will the scars be?
The scars are permanent. I place the main scar low so it can sit under underwear or swimwear. A Fleur de Lis abdominoplasty also leaves a vertical scar up the midline, and a body lift (belt lipectomy) leaves a scar that continues around the trunk. Scars are firm and pink at first, then soften and fade over 12 months or more.
Can I get pregnant after an abdominoplasty (tummy tuck)?
Yes, but a pregnancy can stretch the tissue again and affect the result. If you are planning a pregnancy, it is worth raising at consultation so we can think about timing.
References
- Hocking SL, Scott DA, Remedios ML, Horowitz M, Story DA, Greenfield JR, et al. 2025 ADS/ANZCA/GESA/NACOS clinical practice recommendations on the peri-procedural use of GLP-1/GIP receptor agonists. Anaesth Intensive Care. 2025;53(5):300-306.
- Costa-Ferreira A, Rebelo M, Silva A, Vasconez LO, Amarante J. Scarpa fascia preservation during abdominoplasty: randomized clinical study of efficacy and s*fety. Plast Reconstr Surg. 2013;131(3):644-651.
- Makarawung DJS, Al Nawas M, Smelt HJM, Monpellier VM, Wehmeijer LM, van den Berg WB, et al. Complications in post-bariatric body contouring surgery using a practical treatment regime to optimise the nutritional state. JPRAS Open. 2022;34:91-102.